 Augusta University

 Tim Rausch
In rural Georgia hospitals, where critically injured patients are rare but the stakes could be life-or-death, a Medical College of Georgia at Augusta University training program is bringing advanced trauma skills directly to emergency room staff who need them most.
Over the last year, a team of MCG physicians has successfully piloted a state-funded portable simulation training course, called Rural Interactive Trauma Simulation (or RITS), prompting its renewal this year.
“We’re teaching them how to stabilize a patient in a rural or community setting to get them to that next step,” said Erika Simmerman Mabes, DO, trauma surgeon, and director of surgical simulation and program director of the Surgical Simulation and Education Research Fellowship in the MCG Department of Surgery, the outreach program’s creator.
That next step is often a stable patient being moved to a larger city with a trauma center.
The program addresses a critical gap in rural healthcare: maintaining competency in life-saving procedures that medical staff rarely perform but must execute flawlessly when needed. With 35 rural hospitals, 33 critical access hospitals and 53 Georgia counties without any hospital at all, the challenge is immense.
“In the rural environment, you’re not seeing a ton of patients like you do over there in Augusta,” said Elizabeth V. Atkins, MSN, executive director with the Georgia Trauma Commission who helped fund the program. “They’re what we call low volume, high yield issues when a critically injured patient comes in.”
Atkins, who spent 20 years as a clinical nurse and flight nurse before taking on leadership roles, knows firsthand the challenges rural providers face. She recalls flying to hospitals so remote that one had a screen door as its emergency entrance.
“You only rise to the level of your training,” Atkins said, citing a military saying that captures the essence of the problem. “And so if nobody is out there doing something to help them train and maintain those competencies, then they won’t be able to react in that quick, you know, need to act right now situation where somebody is really sick and they need a procedure.”

Meeting providers where they practice
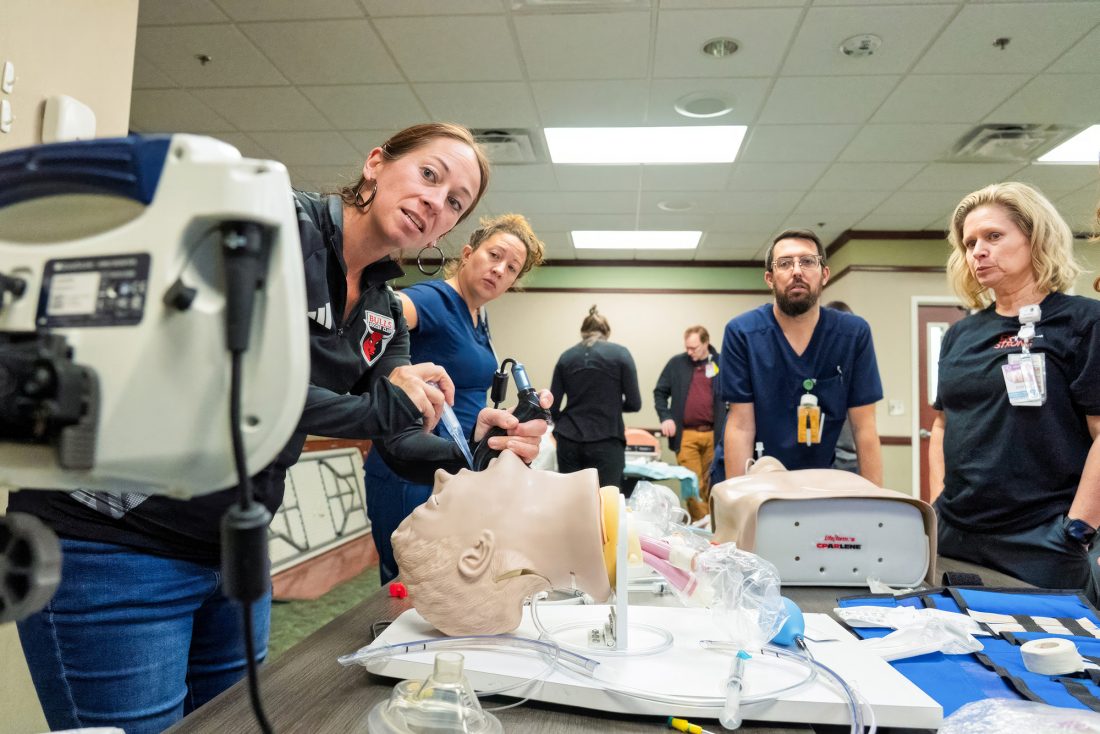
Every RITS course opens with a two-hour interactive classroom didactics segment built around a single deconstructed trauma scenario. Simmerman Mabes, the instructor, plays a video of a critically injured trauma patient, pausing at critical decision-making points to ask participants in the room what they would do next.
The course moves into four hours of procedural stations. Providers rotate through airway management, from basic maneuvers to complex intubations and emergency cricothyrotomy; chest trauma care including chest tube placement and needle decompression; hemorrhage control, covering tourniquet application, pelvic binders and FAST ultrasound exams to asses for internal bleeding; and access in the critically-ill patient, including intraosseous access, central venous access and level one transfuser utilization.
Sessions typically draw 25 to 30 participants, a number Simmerman Mabes considers strong given that most attendees are pulled off active shifts to be there. About half of the host facilities also serve as regional hubs, drawing staff from sister hospitals and freestanding emergency rooms nearby.
The RITS course is intentionally multidisciplinary; Nurses, EMS and flight crews, respiratory therapists, nurse practitioners and multi-specialty physicians that may include family medicine, internal medicine, emergency medicine or surgery providers all rotate through the stations together, a design that reflects how thinly staffed rural emergency rooms actually run.
“How can we help facilitate the decision making and procedural skills and assisting each other?” Dr. Simmerman Mabes asks.
Even when a nurse will not be the one performing an intubation, she said, knowing how to assist effectively can be the difference in an ER running on one or two staff members during a critical case.
The training also covers the resource limits specific to small hospitals. Providers practice securing a fractured pelvis with a folded sheet when a commercial binder is not on hand, and they walk through the realities of an EMS crew that must stabilize and actively resuscitate a patient during an ambulance ride that can stretch one to two hours to the nearest trauma center.
A year of results
The RITS team has trained more than 200 rural healthcare providers. Course evaluations show strong feedback.
The rollout itself has reached more than a dozen communities, including Douglasville, Blue Ridge, Griffin, Hinesville, Albany and Swainsboro. This month it added Blairsville. Thomasville and additional Hinesville sessions are planned for September and December, respectively, with additional stops in Madison and Rome planned into early 2027. Organizers are targeting roughly a dozen courses annually going forward, with expansion planned into northeast and northwest Georgia.
The program has also drawn academic attention beyond Georgia. This year, the team presented outcomes data at the Academic Surgical Congress and the Association for Surgical Education’s Surgical Education Week. A manuscript on the program’s needs assessment and curriculum is currently under review with the Journal of Surgical Research and a separate manuscript covering the pilot year’s outcomes remains in development.
What comes next
The program’s five-year sustainability plan, developed jointly by the Georgia Trauma Commission, the State Office of Rural Health and the Georgia Trauma Foundation, calls for regional training hubs and local instructors at each participating hospital, eventually reducing how often MCG’s team needs to make the drive itself.
An instructor manual now in development would let interested providers at each hospital become assistant instructors, with some eventually leading sessions on their own.
In the future, organizers want to build additional regional hubs at academic medical centers with advanced simulation equipment, similar to what MCG already has, allowing for higher-fidelity training for larger groups. There is also early discussion of linking RITS to MCG’s existing telehealth network, pairing virtual consultations with the in-person training the program already delivers.


 Staff

 Hannah Litteer

 Jaylon Brooks

 Jennifer Hilliard Scott